


Chapter 1 of 5 · Case-Based Learning
Case setup
Case presentation and operative setup
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
QUAD #26 - Use of Ultrashort Echo-Time MRI to Measure Tracheomalacia in Neonates with Esophageal Atresia with Dr. Douglas von Allmen
CCHMC Pediatric Surgery · 5 min · Published Feb 2025
Podcast
Case Based Journal Review: Esophageal Atresia in 2022
17 min · Published Aug 2022
Video
QUAD #10 Pt.3: Advantages of Thoracoscopic Repair of Esophageal Atresia with Dr. Steve Rothenberg
Dr. Steve Rothenberg · Published Jun 2024
Video
JRS TEF SHORT
Dr. Steve Rothenberg · 2 min · Published May 2026
Video
Glycopyrrolate for Anastomtic Dehiscence in Esophageal Atresia
2 min · Published May 2017
Video
Esophageal Atresia & Tracheoesophageal Fistula (EA/TEF) Types Explained for Pediatric Surgery
2 min · Published Sep 2026
Video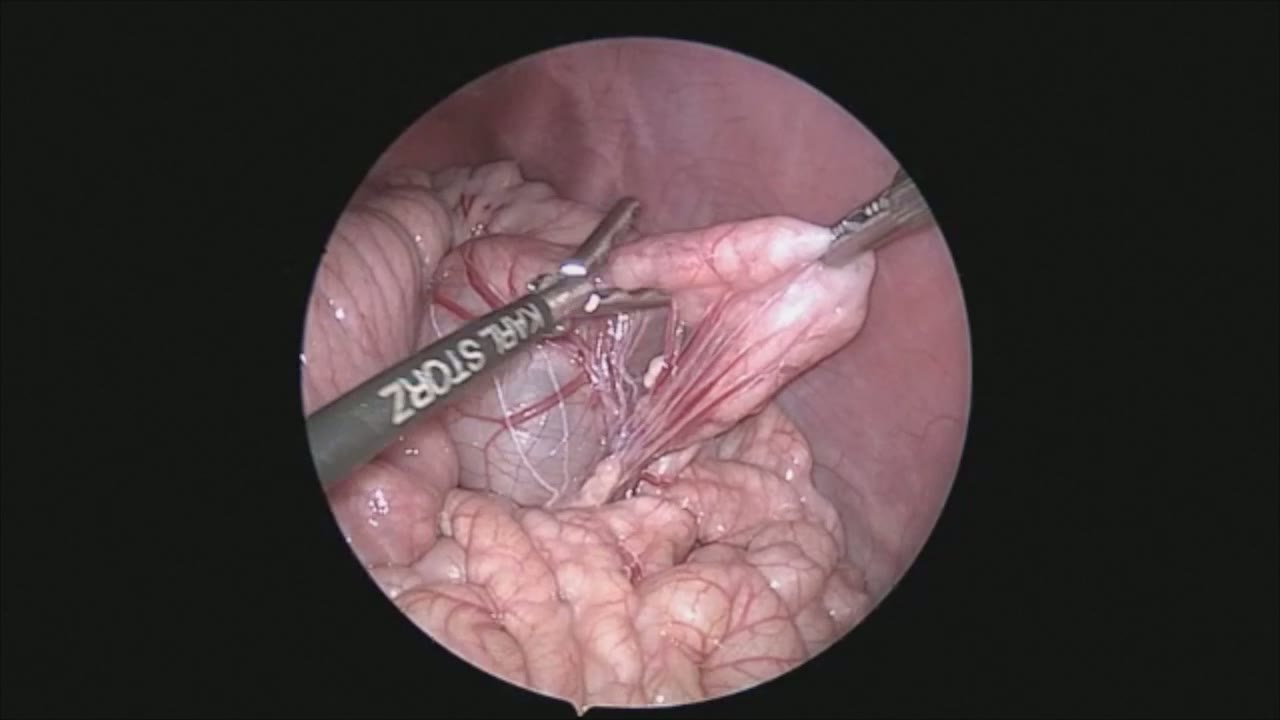
sealer demo
Dr. Steve Rothenberg · 3 min · Published May 2026
Video
pyloric knife
Dr. Steve Rothenberg · Published May 2026
Video
pulm artery LLL
Dr. Steve Rothenberg · 9 s · Published May 2026
Video
plication narrated
Dr. Steve Rothenberg · 6 min · Published May 2026
Video
percuvance redo nissen
Dr. Steve Rothenberg · 5 min · Published May 2026
Video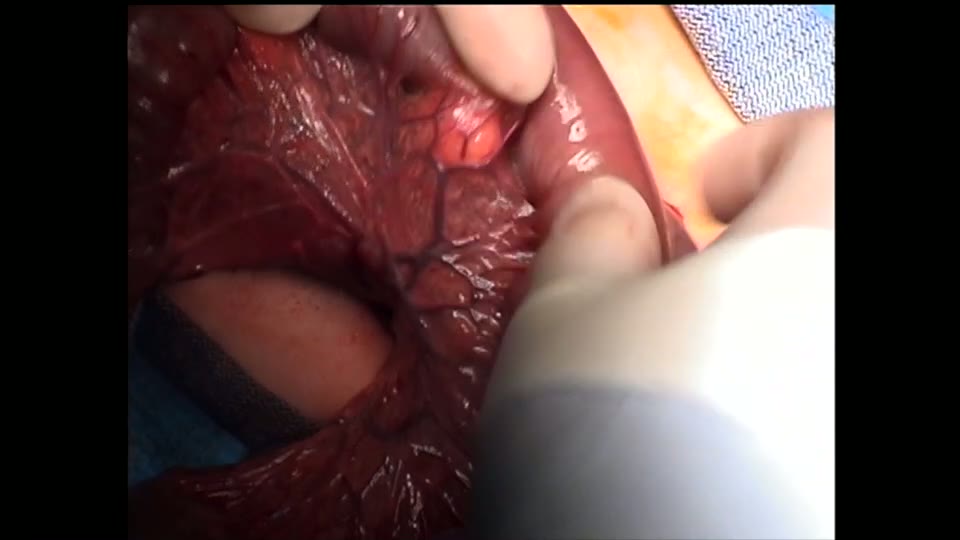
open bowel anast
Dr. Steve Rothenberg · Published May 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
A 28-week premature infant weighing 900 g was born with a tracheoesophageal fistula
The patient underwent successful ligation and gastrostomy tube placement for TEF
The patient developed necrotizing enterocolitis 3 weeks after TEF repair
NEC was treated medically, but the child developed a stricture shown on upper GI at 8 weeks of age
Three ports were used: a 4 millimeter 30 degree scope and two 3 millimeter ports, with the right-handed port later changed to 5 mm for the stapler
A Meckel's diverticulum was discovered while running the bowel proximally from the ileocecal valve
The stricture was located at approximately mid ileum
A loop of bowel was densely adherent to the capsule of the spleen at the point of obstruction
The 3 millimeter sealer was used to gently dissect the bowel off the spleen, preserving the splenic capsule with no bleeding
A small enterotomy was made during mobilization, which was later used to show the exact site of the obstruction
Forceps passed through the enterotomy showed complete obstruction of the bowel at the stricture site
The 5 millimeter stapler lays down 2 millimeter staples in 4 rows which are then divided between two rows equally
A 3-0 Prolene stitch was passed through the anterior abdominal wall and then through the two ends of the bowel to set up a side to side anastomosis, providing excellent exposure and acting as a retractor
A 3-0 Vicryl suture was used intracorporeally to align the proximal end of the anastomosis
The residual enterotomy after stapled anastomosis was closed with a running 3-0 Vicryl suture
Because of the very small intraabdominal space, only a limited portion of the trocar can be inserted into the abdominal cavity
A 3 millimeter bowel clamp was used to compress the base of the Meckel's to ensure all gastric mucosa would be resected
The Meckel's diverticulum had normal mucosa
The thumb of a size 7 glove was used as a manufactured specimen bag for extraction through the 5 millimeter port
The entire operation took 75 minutes and the child tolerated the procedure extremely well
The resected specimen was approximately 3.5 centimeters in length
At one month after resection, the baby was tolerating feeds without problems