


From
StayCurrentMD
Thoracoscopic Repair of Tracheo-esophageal Fistula Tricks: Pediatric Surgery...
With Dr. David Vanderzee & Dr. Jeff Blair
Chapter 1 of 4 · Surgical Management
Partial fistula division
Introduction and technique overview: partial fistula division
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
QUAD #10 Pt.1: History of Thoracoscopic Repair of Esophageal Atresia (EA) & Tracheoesophageal Fistula (TEF) with Dr. Steve Rothenberg
Dr. Steve Rothenberg · 6 min · Published Jun 2024
Video
Tricks - Imperforate Anus and Rectourethral Fistula
45 min · Published Nov 2018
Video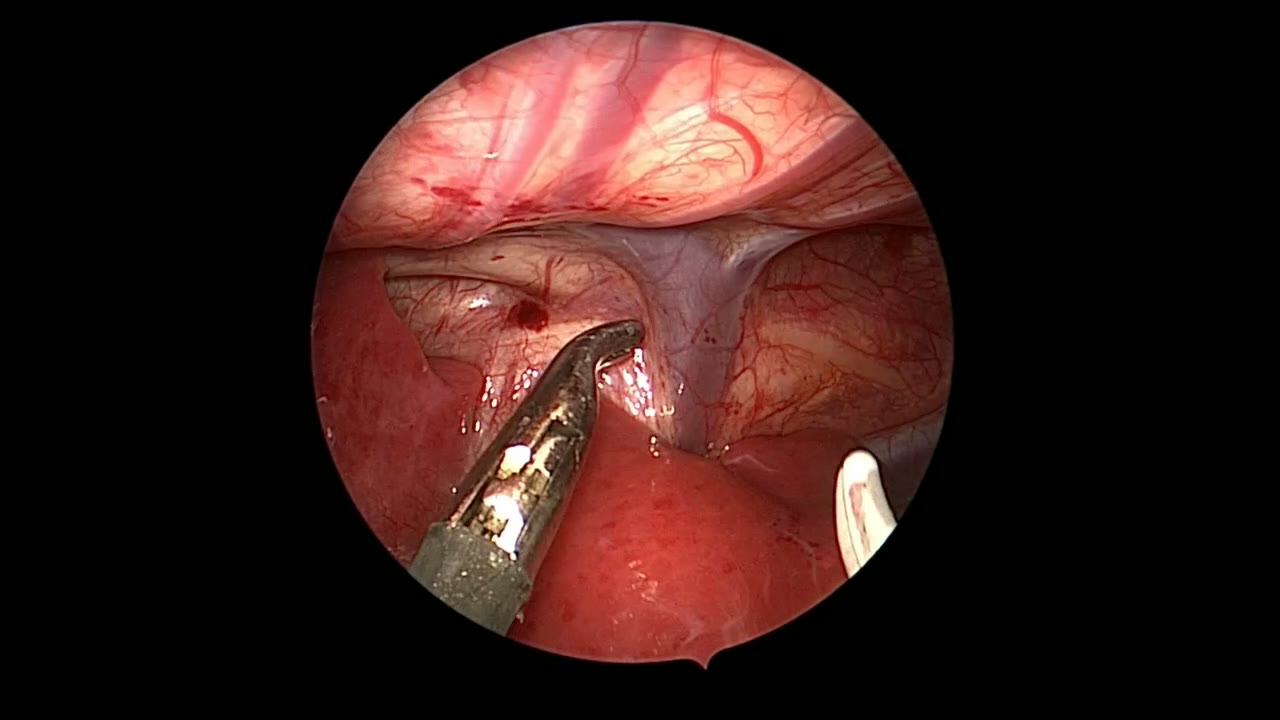
JRS TEF SHORT
Dr. Steve Rothenberg · 2 min · Published May 2026
Video
Tips and Tricks: EA & TEF
Dr. Steve Rothenberg · 9 min · Published Dec 2012
Video
Esophageal Atresia/Tracheoesophageal Fistula Bronchoscopy and Surgical Technique
Dr. Todd Ponsky · 16 min · Published Nov 2021
Video
Esophageal Atresia in Brief: Presentation, Workup, Diagnosis, and Treatment
Dr. Todd Ponsky · Published Feb 2022
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
For thoracoscopic TEF repair, spk_0 assesses the gap between proximal and distal esophagus preoperatively using bronchoscopy (to identify the fistula orifice) followed by X-ray with the bronchoscope in place and a gastric tube, measuring the gap in vertebral body units.
In the presented case, the gap between proximal and distal esophagus was approximately one vertebral body.
The majority of surgeons divide the distal esophagus completely during TEF repair, but spk_0 leaves one quarter of the fistula uncut.
If the distal esophagus is divided completely, it can retract cranially and anastomosis becomes more difficult.
Leaving one quarter of the fistula uncut provides fixation of the distal esophagus and makes it easier to grasp the mucosa during anastomosis.
spk_0 does not cut all of the tip of the proximal esophagus; he leaves one-quarter to one-fifth of the cap of the proximal esophagus to grab with forceps, avoiding grasping the anastomotic site.
If there is a 1-3 vertebral body gap, the assistant can pull the proximal esophagus caudally using the uncut cap.
spk_0 places the first anastomotic stitch in the middle of the posterior wall, not at the edge, finding this easier especially with his technique.
spk_0 uses 6-0 or 5-0 PDS suture for the anastomosis.
The mucosa of both proximal and distal esophagus must be included in the anastomotic stitches; otherwise the patient will have postoperative stenosis.
spk_0 divides the tracheoesophageal fistula completely after placing one or two anastomotic stitches.
spk_0 divides the uncut cap of the proximal esophagus after placing 2-3 anastomotic stitches.
spk_0 does not touch the site of the anastomosis in the proximal and distal esophagus during his technique.
spk_1 tried spk_0's technique after seeing the video in September and found it worked well, though he was uncertain how much he needed the traction provided by the uncut tissue.
spk_1 suggests there is no downside to leaving the last bit of fistula uncut initially; if the stitch sets up perfectly, it can be taken, and if not, it can be cut and the anastomosis completed.
David Vanderzee (spk_2) thinks leaving the fistula partially connected to the trachea initially might be helpful, but his group does not do it.
David Vanderzee's group uses a transfixing suture to close the fistula to ensure it does not come off, and never uses clips because they tend to hook behind the anastomotic suture.
For type C esophageal atresia with considerable length, David Vanderzee's group puts in two sutures, makes them into sliding knots, and slowly brings the esophageal ends together, dividing tension between the two ends.
David Vanderzee's group finalizes the posterior anastomosis before putting through a tube and closing the anterior wall.
Jeff Blair (spk_3) speculates that in the next decade, mechanical devices may be used to grab and seal the lower esophageal pouch via the upper pouch, possibly with thoracoscopic or imaging facilitation.
Suet (spk_4) found it much easier to identify the fistula laparoscopically (likely meant thoracoscopically) and to appreciate how much esophagus to leave on the tracheal side.
Suet found dissecting the upper segment of the esophagus difficult, particularly in handling the esophagus without damaging the wall needed for anastomosis.
Sharif (spk_5), who started doing thoracoscopic TEF a year ago and has done three cases, finds the dissection and fistula division phase easy but the anastomotic phase difficult.
spk_1 has had a clip erode into the esophagus in his experience.
spk_1 uses metal clips for fistula closure.
spk_1 has tried Weck Hema-lock clips 2-3 times but finds the clip applier too large, reducing visualization compared to the metal clip applier.
Weck Hema-lock clips are not easy to remove if their position is unsatisfactory.
spk_0 believes that if the fistula is clipped very tightly, it will erode the muscle of the esophagus, but if the clip is applied just to oppose (not crush), it does not cause erosion.
Tight clipping may crush the esophageal muscle, erode it, and cause recurrence of the fistula.
Mark Wolkan presented a technique from Atlanta in which a stitch is placed through the chest wall, through the proximal esophageal end, through the distal end, and back out through the chest wall, and held up during anastomosis.
Steve Rothenberg uses clips routinely for TEF repair.
There have been several instances where clips seem to erode or be implicated in TEF recurrences.
Steve Rothenberg, who has the largest experience with thoracoscopic TEF, has never had a clip erode.