


Chapter 1 of 6 · Fundamentals
Introduction
Introduction and Series Context
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Podcast
Hirschsprung Disease â PediaCast 287
Marc Levitt · 38 min · Published May 2014
Video
DrBeen Medical Lectures: Dr. Marc Levitt, MD Discusses Hirschsprung Disease
53 min · Published Dec 2022
Podcast
The Colorectal Quiz Episode 10: Total Colonic Hirschsprung Disease Part 1
12 min · Published Apr 2021
Video
Evaluation & Management Of Hirschsprung's Disease
44 min · Published Nov 2018
Video
Meconium Plug Syndrome (MPS)
Published Mar 2020
Video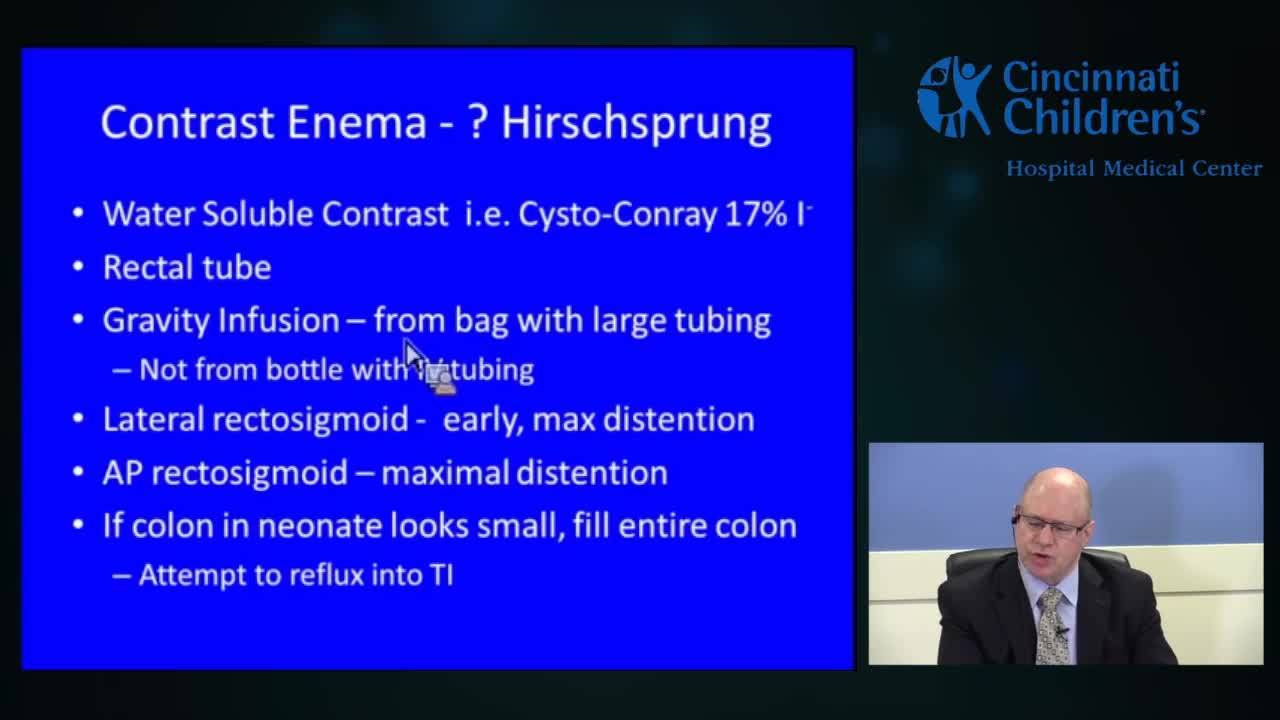
Contrast Enema for Hirschsprung Disease
11 min · Published Feb 2015
Video
Validation of an anorectal malformation trainer - Can a high-fidelity model simulate real life?
1 min · Published Jun 2026
Video
Complications and Long-Term Outcomes of Patients With Cloacal Malformation After Bowel Neovagina...
1 min · Published Jun 2026
Video
Safety and utility of long-acting steroid injection for management of post-operative stricture...
1 min · Published Jun 2026
Video
Association Between Social Determinants of Health and Choice of Urinary Reconstruction in Children
1 min · Published Jun 2026
Video
The Perineal Body Preserving PSARP (PPP)
11 min · Published Jun 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Colorectal Quiz Ep. 50 -16th Annual European Pediatric Colorectal & Pelvic Reconstruction Conference
Marc Levitt · Published Mar 2026
Podcast
Colorectal Quiz: Episode 50 - 16th Annual European Pediatric Colorectal and Pelvic Reconstruction Conference, Stockholm, Sweden, October 2025 - What did we learn?
24 min · Published Mar 2026
Video
Colorectal Quiz Episode 33: Cloaca Exstrophy
Marc Levitt · 22 min · Published Sep 2025
Video
The Colorectal Quiz Episode 21: The History of Hirschsprung Disease
Marc Levitt · 15 min · Published Sep 2025
Video
Colorectal Quiz: Episode 49 – Collaborating for Kids: Colorectal & Pelvic Care (with Help from AI)
Marc Levitt · 40 min · Published Jul 2025
Podcast
Colorectal Quiz: Episode 49 - Collaborating for Kids: Colorectal & Pelvic Solutions (with a Little Help from AI)
Marc Levitt · 40 min · Published Jul 2025
Podcast
Long-term obstetric and gynecologic care for patients with anorectal malformations
21 min · Published Sep 2026
Podcast
Post-pubertal gynecologic evaluation and management of patients with anorectal malformations
22 min · Published Sep 2026
Podcast
Pre-pubertal gynecologic evaluation and management of patients with anorectal malformations
23 min · Published Sep 2026
Podcast
Methods of gynecologic evaluation for patients with anorectal malformations
21 min · Published Sep 2026
Podcast
Gynecologic care in patients with anorectal malformations: A primer and call to action
18 min · Published Sep 2026
Podcast
Evaluation and Management of Postsurgical Patient With Hirschsprung Disease Neurogastroenterology & Motility Committee: Position Paper of North American Society of Pediatric Gastroenterology, Hepatology, and Nutrition (NASPGHAN)
17 min · Published Sep 2026
What the experts said
Maternal magnesium sulfate used to slow delivery can cause neonatal abdominal distention that mimics Hirschsprung disease
Maternal opiates can cause neonatal abdominal distention mimicking Hirschsprung disease
Hypothyroidism can present with neonatal abdominal distention similar to Hirschsprung disease
Small left colon syndrome associated with maternal diabetes can mimic Hirschsprung disease
Contrast enema should not be performed in the presence of enterocolitis due to risk of perforation
Rectal irrigations before contrast enema do not change the result of the contrast study
The contrast study serves as a roadmap for surgery rather than a definitive diagnostic tool for Hirschsprung disease
In Hirschsprung disease, the aganglionic rectum appears narrow due to spasm and inability to relax, while the ganglionated proximal bowel is dilated, creating the recto-sigmoid ratio
Hyperperistalsis and tortuosity in the rectum on contrast enema is a classic finding in Hirschsprung disease, reflecting hypercontractility of the aganglionic segment
The exact location of the transition zone cannot be precisely determined on contrast study
Suction rectal biopsy is appropriate for neonates and does not require open biopsy in the operating room
Three good biopsy specimens should be obtained for pathologic evaluation
Quick diff staining highlights ganglion cells better than standard H&E staining
The diagnostic criteria for Hirschsprung disease at the Washington institution is absence of ganglion cells in 100 pathologic levels
If a single ganglion cell is found on biopsy, the diagnosis is not Hirschsprung disease regardless of ganglion cell density
Nerve trunk hypertrophy is defined as nerve trunks greater than 40 microns in diameter
Pathologists should measure nerve trunks in rectal biopsies to confirm hypertrophy
A pathology report showing no ganglion cells without comment on nerve hypertrophy is not satisfactory for surgical decision-making
Patients have been incorrectly operated on for Hirschsprung disease based on pathology reports showing no ganglion cells but lacking nerve hypertrophy documentation
Everyone is physiologically aganglionic in the zone of the anal canal
Hypertrophic nerves are not found in the anal canal zone, so absence of ganglion cells there without nerve hypertrophy does not indicate Hirschsprung disease
Presence of squamous epithelium in a rectal biopsy confirms the biopsy was taken too low (in the anal canal)
The optimal location for rectal biopsy is 0.5 to 1 cm above the crypts to ensure columnar epithelium
The crypts are located above the dentate line, so optimal biopsy location is at least 1-2 cm above the dentate line
Infants presenting with Hirschsprung-like symptoms who have ganglion cells but numerous eosinophils on biopsy may have allergic colitis