


From
StayCurrentMD
Abdominal Wall Defects: Update Course 2013
Chapter 1 of 7 · Acute Management
Delivery planning
Prenatal Management and Delivery Planning for Gastroschisis
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video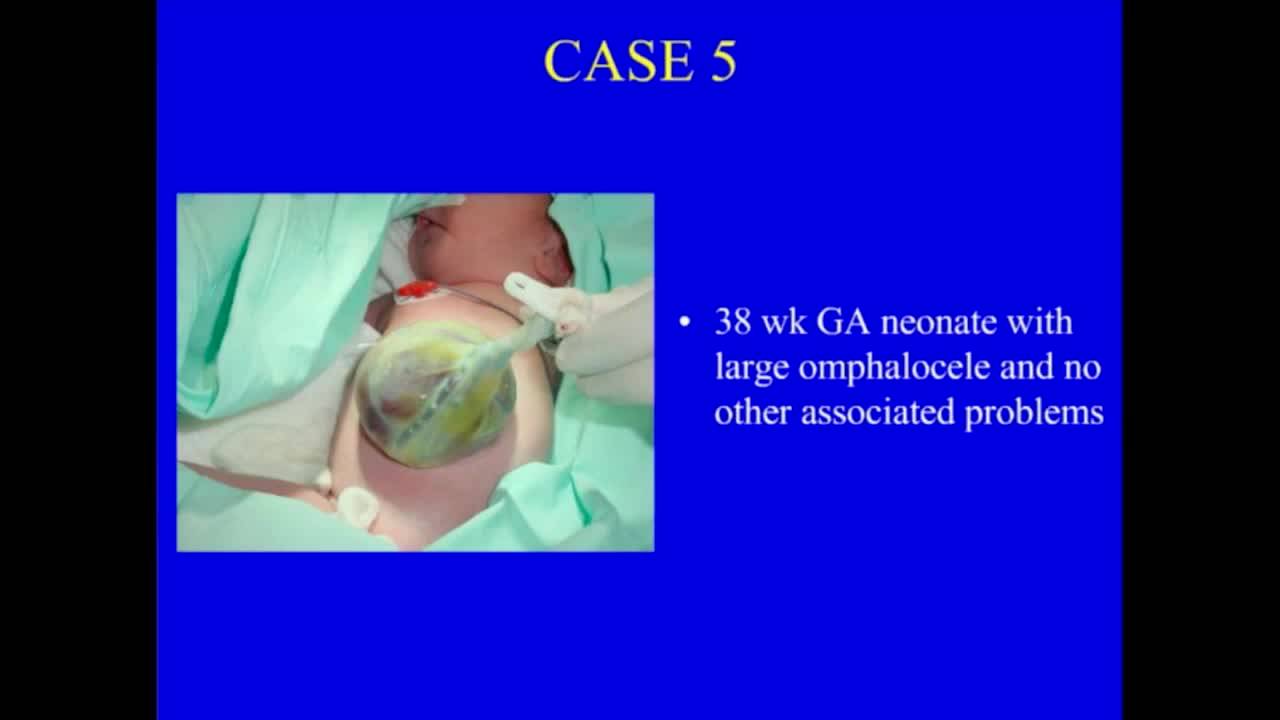
Abdominal Wall Defects
37 min · Published Nov 2018
Podcast
Abdominal Wall Defects with Dr. Jacob Langer
52 min · Published Dec 2016
Video
Gastroschisis: Advanced Practice Providers
43 min · Published Feb 2014
Video
Staged Closure of Gastroschisis with Spring-loaded Silo
27 min · Published Feb 2020
Video
Gastroschisis - Clinical Practice Updates
Published Sep 2020
Video
BOB in Ped Surg 2023 - IBEROAMERICANA Winner - Lourenzo Sbragia, MD
Published Feb 2023
Video
Impact of social determinants of health on outcomes in pediatric short bowel syndrome...
43 s · Published Aug 2026
Video
Advancements in Pediatric Intestinal Failure: Innovative Therapies and Improved Outcomes
17 min · Published Aug 2026
Podcast
Update Course Rewind: Omphalocele & Gastroschisis 2020
Miguel Guelfand · 15 min · Published Jul 2026
Video
Update Course Rewind 2025: Updates in NEC Management
11 min · Published Jul 2026
Video
Availability, utilization, and barriers to bowel ultrasound for necrotizing enterocolitis...
55 s · Published Jul 2026
Video
Malrotation and Volvulus with Trinity
Dr. Steve Rothenberg · 8 min · Published May 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
Most of the damage to the intestine in gastroschisis occurs in the last few weeks of pregnancy, based on animal studies and clinical studies
The age at spontaneous onset of labor for gastroschisis pregnancy is 3 weeks earlier than the general population
About half of gastroschisis pregnancies go into labor spontaneously before 37 weeks
No perinatal center in Canada was doing routine cesarean sections for gastroschisis based on a national survey
15 or 20 years ago, routine cesarean section for gastroschisis was pretty much the standard of care
Using a pre-formed silo allows gentle reduction of gastroschisis bowel without trauma, and in about a third of cases the bowel can be reduced immediately and the silo removed
Waiting for gastroschisis babies to lose their first 10% of body weight reduces bowel edema and makes reduction easier
Leaving a silo on for more than a day causes the fascial defect to get much bigger
Using plastic closure (non-surgical closure) for gastroschisis gives extremely good results, often with a small umbilical hernia that closes by age 2
There are two kinds of intestinal atresia in gastroschisis: early-developing atresia not always associated with bowel thickening, and late-occurring atresia from a very small abdominal wall defect
Bringing an ostomy out through the umbilicus avoids additional scars and makes subsequent closure easier
Gord Cameron in Hamilton in the 1980s was the first to describe umbilical ostomies
At 4 weeks post-gastroschisis repair with feeding intolerance, waiting longer is reasonable as the bowel may still be recovering from motility disorder
At 8 weeks post-repair with persistent feeding intolerance, exploration is warranted to rule out mechanical obstruction
For large omphalocele, attempting to remove the sac and close primarily can lead to inability to achieve closure and need for prosthetic patch
The Schuster repair uses mesh sutured to fascia over intact omphalocele sac with gradual closure, eventually allowing primary repair
For large omphalocele, patch covered by skin or skin coverage alone is better than paint-and-wait which takes months
Lateral component separation makes it easier to bring fascial edges together in omphalocele repair
Antibiotic ointment on omphalocele sac keeps it supple, and using 4x4s with Ace wrap compression can gradually reduce the defect
Ventilatory parameters are the most reliable measure for assessing safe closure tension
Bladder pressure measurement in tiny newborns is unreliable and cannot be trusted consistently
Intragastric pressure monitoring via NG tube is easy to perform in the OR and provides useful guidance, with 20 as a suggested threshold
For giant omphalocele in older children, enlarging the fascial defect and allowing staged closure over time without forcing reduction prevents abdominal compartment syndrome
In older children with giant omphalocele, the abdomen does not expand as rapidly as in newborns and requires more time between stages
When opening the fascial ring in giant omphalocele, opening inferiorly avoids encountering hepatic veins at the superior aspect
Dr. Abello uses Duoderm wrapped around omphalocele and tightens it daily to achieve gradual reduction
Botox has been used successfully by adult hernia surgeons to relax muscle and facilitate closure of large ventral hernias