


From
Colorectal Channel
The Colorectal Quiz Episode 3.5: Proximal Hirschsprung Disease
hosted by Dr. Rod Gerardo & Dr. Todd Ponsky
Chapter 1 of 5 · Case-Based Learning
Case recap
Introduction and Case Recap
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Podcast
The Colorectal Quiz Episode 4
Marc Levitt · 19 min · Published Feb 2021
Video
Hirschsprung Disease: Update Course 2013
38 min · Published Sep 2013
Video
Update Course Rewind 2025: Hirschsprung’s Pull-Through: Why Family Training May Save Lives
2 min · Published May 2026
Podcast
The Colorectal Quiz Episode 10: Total Colonic Hirschsprung Disease Part 1
12 min · Published Apr 2021
Video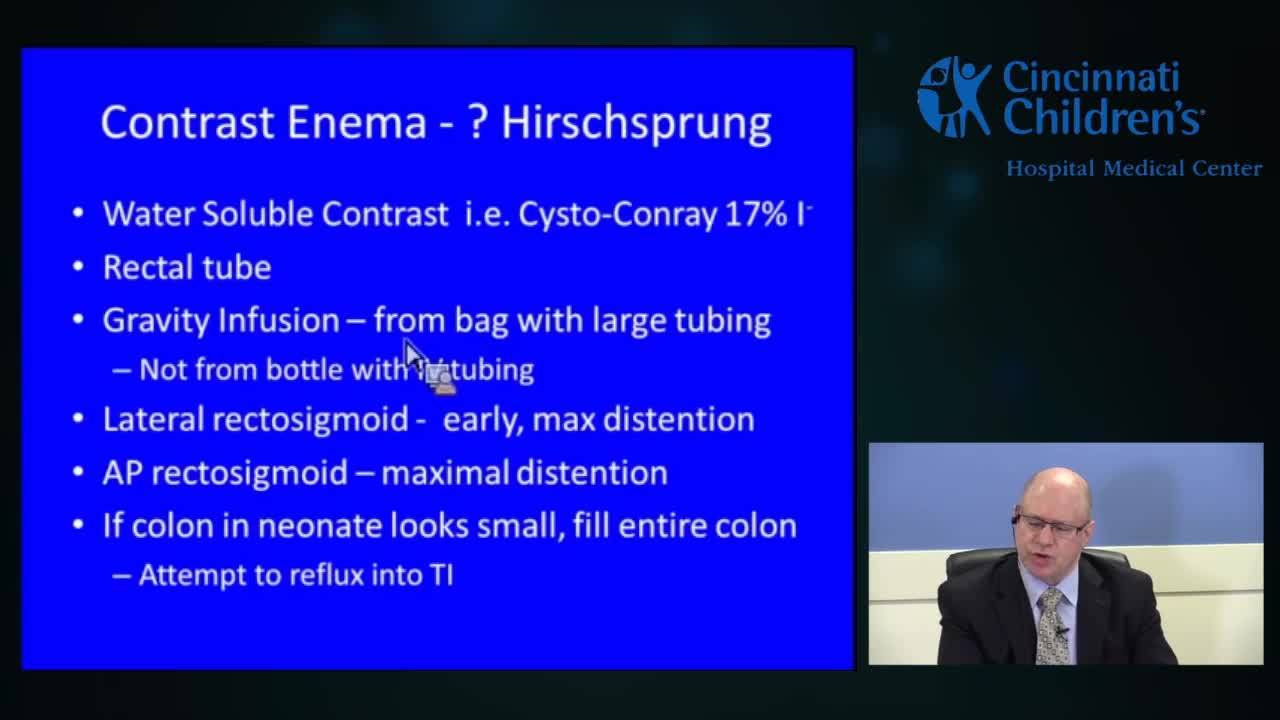
Contrast Enema for Hirschsprung Disease
11 min · Published Feb 2015
Podcast
Colorectal Quiz Episode 3: Hirschsprung Disease
20 min · Published Feb 2021
Video
Validation of an anorectal malformation trainer - Can a high-fidelity model simulate real life?
1 min · Published Jun 2026
Video
Complications and Long-Term Outcomes of Patients With Cloacal Malformation After Bowel Neovagina...
1 min · Published Jun 2026
Video
Safety and utility of long-acting steroid injection for management of post-operative stricture...
1 min · Published Jun 2026
Video
Association Between Social Determinants of Health and Choice of Urinary Reconstruction in Children
1 min · Published Jun 2026
Video
The Perineal Body Preserving PSARP (PPP)
11 min · Published Jun 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Podcast
Long-term obstetric and gynecologic care for patients with anorectal malformations
21 min · Published Sep 2026
Podcast
Post-pubertal gynecologic evaluation and management of patients with anorectal malformations
22 min · Published Sep 2026
Podcast
Pre-pubertal gynecologic evaluation and management of patients with anorectal malformations
23 min · Published Sep 2026
Podcast
Methods of gynecologic evaluation for patients with anorectal malformations
21 min · Published Sep 2026
Podcast
Gynecologic care in patients with anorectal malformations: A primer and call to action
18 min · Published Sep 2026
Podcast
Evaluation and Management of Postsurgical Patient With Hirschsprung Disease Neurogastroenterology & Motility Committee: Position Paper of North American Society of Pediatric Gastroenterology, Hepatology, and Nutrition (NASPGHAN)
17 min · Published Sep 2026
What the experts said
The plain abdominal x-ray showed a big right colon, prominent transverse colon, and a compressed left colon with small lumen, along with possible small bowel dilation.
It is hard on a newborn film to really discern small and large bowel, and you can get fooled.
A baby with bilious emesis and non-classic abdominal x-ray could have had distal air and then had a volvulus, requiring urgent upper GI to rule out malrotation before contrast enema.
A limited upper GI was performed and ruled out malrotation in this child.
The contrast enema showed an impressive right colon with transverse colon tapering off, and a transition zone probably somewhere in the transverse colon.
Patients with proximal Hirschsprung disease are at risk of perforation, usually in the cecum.
To get a perforation, you need distension, and if you have a transition zone at the hepatic flexure, then all the pressure is in the right colon.
A baby that doesn't have a competent ileosecal valve might be saved from perforation because pressure can decompress into the small bowel.
You are obligated at some point, maybe after resuscitation, to get a rectal biopsy in a patient with suspected Hirschsprung disease.
If the transition zone is at the hepatic flexure, you can predict that enough pressure builds up in the right colon to have the cecum perforate.
You rarely get a perforation in a more standard sigmoid level transition zone.
A suction rectal biopsy confirmed the diagnosis of Hirschsprung disease in this patient.
Proximal Hirschsprung disease and distal Hirschsprung disease require two different operative approaches.
A one-day-old full-term infant weighing 3.9 kilograms presented with significant abdominal distension and bilious emesis.
If a child is sick with bilious emesis and distension, resuscitation should be the first step before diagnostic workup.